Snake Envenomation in Dogs and Cats: Clinical Signs, Diagnosis, and Treatment

Snake envenomation is a challenging emergency encountered in companion animal practice, with incidence varying by geographic region and season. Snake envenomation can rapidly progress from localized tissue injury to life-threatening cardiovascular collapse, coagulopathy, and multiple organ dysfunction. Successful management of these patients requires understanding venom pathophysiology, recognizing species-specific clinical signs, implementing evidence-based supportive care, and educating clients about prevention.

Understanding Snake Venom

Snake venom is a complex mixture of proteins, enzymes, and peptides that vary among species. In North America, pit vipers, including rattlesnakes (Crotalus spp.), copperheads (Agkistrodon contortrix), and cottonmouths (Agkistrodon piscivorus), account for the majority of clinically significant envenomations in dogs and cats. Coral snake bites occur less frequently and produce predominantly neurotoxic effects.

Most pit viper venoms contain combinations of cytotoxins, hemotoxins, myotoxins, and vasoactive compounds. These toxins disrupt vascular integrity, activate inflammatory pathways, damage skeletal muscle, and impair normal coagulation. Variable venom composition between species, and even individual snakes, means clinical presentation varies.

Clinicians also need to remember that not every bite results in venom injection. “Dry bites” occur when little or no venom is delivered, making reassessment and patient monitoring essential before determining a treatment plan and prognosis.

Clinical Presentation

The face and distal limbs are the most common bite locations because curious pets frequently investigate snakes and their habitats with their noses. Local tissue injury often develops within minutes with signs of pain, rapidly progressive edema, erythema, ecchymosis, and hemorrhagic discharge. Tissue damage from fang penetration is usually minimal but the swelling extending from the bite region can be severe.

If venom enters systemic circulation, affected patients may develop:

  • Tachycardia
  • Hypotension
  • Weakness
  • Vomiting
  • Hypersalivation
  • Tachypnea
  • Cardiac arrhythmias
  • Altered mentation
  • Coagulopathy
  • Shock

Coral snake envenomation presents differently. Progressive lower motor neuron dysfunction, generalized weakness, cranial nerve deficits, and respiratory paralysis predominate, while local swelling may remain relatively mild.

Diagnostic Evaluation

Snake envenomation is a clinical diagnosis based primarily on history and physical examination. Initiate treatment promptly rather than waiting for confirmation of snake species.

Baseline diagnostics provide valuable information for monitoring disease progression and identifying complications. Recommended testing includes a complete blood count w/ red blood cell morphology evaluation, serum biochemistry profile, electrolyte analysis, coagulation testing, blood pressure, urinalysis, and electrocardiography.

Common laboratory abnormalities include thrombocytopenia, echinocytosis, prolonged clotting times, elevated creatine kinase (CK), hemoconcentration (initial) or anemia (progressive), and evidence of acute kidney injury in severely affected patients. Because coagulopathies may evolve over several hours, repeat laboratory evaluation often proves more informative than a single initial assessment.

Treatment Priorities

Initial stabilization follows standard emergency principles, with attention to airway, breathing, and circulation before focusing on the bite itself. Establish intravenous access immediately, followed by isotonic crystalloid therapy to support perfusion and correct any hypotension.

Adequate analgesia is important because envenomation causes immense pain. Opioids (e.g., fentanyl, hydromorphone) generally provide effective pain control without interfering with coagulation or renal perfusion (though avoid morphine due to risk of histamine release). Avoid NSAIDs due to potential platelet and renal side effects. Glucocorticoids are contraindicated and antihistamines are ineffective. Antibiotics are usually not needed, but monitor wound for signs of infection.

Clinicians should avoid outdated first-aid recommendations such as tourniquets, incision suction, cryotherapy, or attempts to extract venom. These interventions fail to improve outcomes and may worsen tissue injury.

The Role of Antivenom

Antivenom provides the only specific treatment capable of neutralizing circulating venom and limiting progression of systemic disease. Contrary to a common misconception, antivenom does not reverse tissue damage that has already occurred. Instead, it prevents additional venom from binding to target tissues, making early administration particularly valuable.

Patients receiving antivenom require continuous monitoring during infusion due to risk of hypersensitivity reactions, although modern veterinary antivenoms have greatly improved safety profiles. Counsel owners on this risk, but the benefits are generally considered to far outweigh the chance of reaction.

Monitoring for Delayed Complications

Successful management extends beyond the initial emergency period. Patients require repeat examinations to monitor tissue swelling, perfusion, coagulation status, and systemic organ function throughout hospitalization.

Potential complications include:

  • Disseminated intravascular coagulation (DIC)
  • Acute kidney injury
  • Cardiac arrhythmias
  • Tissue necrosis
  • Secondary wound infection
  • Hypocoagulable state

Veterinary technicians play a particularly important role by performing frequent pain assessments, monitoring limb circumference when appropriate, maintaining intravenous access, recognizing changes in patient status, and communicating subtle clinical deterioration to the attending veterinarian.

Client Education: Preventing Future Snake Encounters

Although it is not always possible to avoid snake bites, client education can significantly reduce exposure risk, particularly in endemic regions. Encourage owners to keep dogs on designated trails and leashed when hiking in areas known to harbor venomous snakes. Maintaining yards by trimming tall grass, removing brush piles, and limiting rodent populations to make residential properties less attractive to snakes.

Advise owners to avoid allowing dogs to investigate rock piles, dense vegetation, or fallen logs during warmer months when snakes remain most active. Owners of hunting and working dogs may also benefit from discussing region-specific snake avoidance training programs where available.

Clients should understand that it is unnecessary, and potentially dangerous, to attempt to identify, capture, or kill the snake. Instead, they must move both themselves and their pet away from the snake safely and seek immediate veterinary care.

Finally, emphasize that time is one of the most important prognostic factors. Owners should never attempt home treatment or delay evaluation while waiting to see how things progress.

Early Intervention and Client Education Improve Outcomes

Veterinarians and veterinary technicians play a vital role in helping pet owners recognize the urgency of snake envenomation and seek immediate veterinary care. Through prompt assessment, evidence-based treatment, and proactive client education about snake avoidance and prevention, veterinary teams can reduce complications, improve patient outcomes, and help keep pets safe in regions where there are venomous snakes.

More from Zuku Learning:

Corn Cob Foreign Bodies in Dogs: A Common Surgical Emergency

One of the most classic foreign bodies in small animal practice is the corn cob. Although owners often assume a cob is “natural” and therefore digestible, veterinary teams know otherwise. Corn cobs are among the most frequent causes of complete small intestinal obstruction in dogs, requiring emergency surgery and carrying the potential for intestinal perforation, septic peritonitis, and prolonged hospitalization.

Why are Corn Cobs so Dangerous?

Unlike many ingested foreign objects, corn cobs possess several characteristics that make spontaneous passage unlikely. Once free of kernels, the remaining fibrous cob is composed largely of cellulose and lignin, making it highly resistant to digestion. Once swallowed, the cob readily absorbs fluid and becomes larger and softer without breaking apart. Its cylindrical shape allows it to move through the stomach but frequently results in obstruction at narrower sections of the small intestine, particularly the jejunum or ileum.

Dogs often ingest corn cobs whole after gaining access to trash, compost bins, picnic leftovers, or barbecue waste. Labrador and golden retrievers, beagles, and other food-motivated breeds are common culprits, although any dog may be affected.

Clinical Presentation

Clinical signs depend on the degree and duration of obstruction but often develop within 24 to 72 hours after ingestion. Affected dogs commonly present with repeated vomiting, anorexia, lethargy, abdominal pain, and dehydration. As obstruction persists, vomiting becomes more frequent, electrolyte abnormalities worsen, and abdominal discomfort increases. Perforation and septic peritonitis dramatically worsen prognosis and may result in cardiovascular compromise, fever, hypotension, and signs of septic shock.

Differential Diagnoses

Eighty percent of GI obstruction in dogs is a result of the ingestion of foreign objects, with the rest due to intestinal intussusception or neoplasia. Corn cob obstruction is on the differential list for any dog presenting with suspected obstruction. Other common causes include:

  • Linear foreign bodies (e.g., rope, towel, rug material)
  • Fruit pits
  • Bones
  • Toys or balls
  • Socks and other textiles
  • Rocks

A complete history and advanced imaging can help distinguish these conditions before surgery.

Diagnostic Approach

A thorough history often provides the most valuable diagnostic clue. Owners may witness ingestion directly or report that corn cobs disappeared after a family cookout or outdoor gathering.

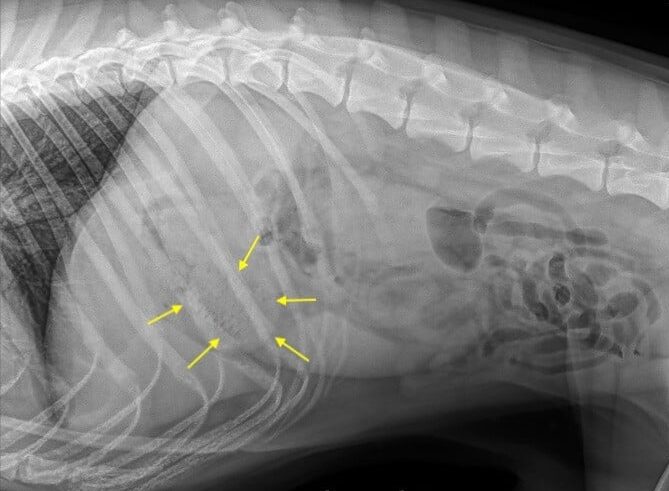
Because many foreign objects are poorly radiopaque, survey abdominal radiographs frequently reveal only indirect evidence of obstruction rather than the foreign body itself. Findings may include gastric distension, fluid-filled small intestinal loops, segmental intestinal dilation, or gas accumulation proximal to the obstruction. While not radiodense, corn cobs do have a classic reticulated pattern due to gas trapping along the cob and can often be identified on radiographs.

corn cob vertical
corn cob horizontal
Images courtesy of Catherine Reiss, DVM

Abdominal ultrasonography by an experienced operator can provide confirmation of obstruction if radiographs are inconclusive. The cob, as with other obstructive objects, typically appears as a hyperechoic intraluminal structure with marked distal acoustic shadowing and associated intestinal distension. Ultrasound also allows clinicians to assess intestinal wall integrity, evaluate other organs, and check for evidence of perforation.

Laboratory abnormalities are nonspecific but may include dehydration, hemoconcentration, and electrolyte derangements.

Treatment: Surgery is Usually Required

Unlike some foreign bodies, corn cobs rarely successfully pass through the entire gastrointestinal tract without intervention. If the owner immediately recognizes ingestion and the cob remains within the stomach, the veterinarian may attempt to induce emesis. Endoscopic retrieval may be possible in appropriately selected patients when emesis is unsuccessful. However, once the foreign body causes obstruction of the small intestine, exploratory laparotomy is the treatment of choice.

During surgery, the surgeon must carefully evaluate the affected bowel for viability before removing the obstruction. A simple enterotomy is often sufficient when the intestine remains healthy. However, prolonged obstruction may compromise blood supply, necessitating intestinal resection and anastomosis. Clinicians should inspect the entire gastrointestinal tract for additional foreign material before closure, particularly in dogs with a history of dietary indiscretion.

Postoperative Care

Successful recovery depends on more than surgical removal of the obstruction. Patients require aggressive fluid therapy, multimodal analgesia, antiemetic therapy, nutritional support, and close monitoring for postoperative complications.Veterinary technicians play a critical role during recovery by monitoring pain scores, maintaining intravenous infusions, tracking gastrointestinal function, encouraging early nutritional intake, and educating owners about postoperative care.

Most uncomplicated enterotomies carry an excellent prognosis, while intestinal resection, delayed presentation, or septic peritonitis significantly increase morbidity and mortality.

Client Education: Prevention Starts at Home

Corn cob foreign bodies are largely preventable, making client education one of the most valuable aspects of these cases.Owners frequently underestimate the danger because some owners feed corn as a treat without issue. It is important to explain that it is the cob, not the kernels, that is the problem. Advise clients to dispose of corn cobs immediately after meals, secure trash containers, and keep compost piles inaccessible to pets. Backyard barbecues, picnics, and holiday gatherings create ideal opportunities for accidental ingestion, particularly in food-motivated breeds.

Owners should also understand that waiting for the cob to “pass on its own” can significantly worsen prognosis. Dogs that vomit repeatedly after known or suspected ingestion strongly benefit from immediate veterinary evaluation before intestinal compromise develops.

Veterinary Teams can Help Prevent this Common Surgical Emergency

Veterinarians and veterinary technicians play an important role in helping owners understand that corn cobs are far more than a harmless table scrap. Through client education, early recognition of intestinal obstruction, and prompt surgical intervention when needed, veterinary teams can help prevent serious complications and improve outcomes for dogs affected by this common but preventable emergency.

More from Zuku Learning:

Smoke Inhalation in Pets During Wildfire Season: What Every Veterinarian Should know

Wildfire season creates serious health risks for people and pets alike. While burns often receive the most attention, pets do not have to come into contact with flames to become critically ill. Smoke inhalation is one of the most dangerous consequences of wildfire exposure, damaging the respiratory tract, reducing oxygen delivery, and triggering life-threatening complications.

Educate owners about the effects of wildfire smoke and the early clinical signs of smoke inhalation so they know to seek veterinary treatment before the condition worsens.

Why Wildfire Smoke is So Dangerous

Wildfire smoke contains a complex mixture of toxic gases and microscopic particles. Carbon monoxide, cyanide, particulate matter (PM2.5), and chemicals released from burning vegetation, plastics, and buildings can all contribute to illness. As pets inhale these irritants, inflammation develops throughout the respiratory tract. The smallest particles travel deep into the lungs, where they disrupt normal gas exchange and make breathing increasingly difficult. Toxic gases such as carbon monoxide also reduce the blood’s oxygen-carrying capacity, placing every organ under stress.

Even pets that spend only a short time outdoors during heavy smoke events may experience harmful effects.

Which Pets Face the Greatest Risk?

Any pet can suffer from smoke inhalation, but certain breeds of dogs and cats have less reserve when their respiratory system becomes compromised. Brachycephalic breeds, including bulldogs, pugs, Boston terriers, and Persian cats, often struggle because their shortened airways already limit airflow. Senior pets, young animals, and those with asthma, chronic bronchitis, or heart disease also face a higher risk of developing severe complications.

Working dogs and highly active pets may inhale larger amounts of smoke simply because they breathe more deeply during exercise. During periods of poor air quality, limiting outdoor activity protects all pets but is especially important for these vulnerable groups.

Recognizing the Clinical Signs

Some pets begin coughing or breathing heavily immediately after smoke exposure. Others appear normal at first but gradually worsen over the next 24 to 72 hours as airway inflammation progresses. Monitor for:

  • Persistent coughing
  • Rapid or labored breathing
  • Wheezing
  • Excessive panting
  • Unusual fatigue

Cats may breathe with their mouths open, which always warrants immediate intervention. You may also notice soot around the nose or mouth, irritated eyes, excessive drooling, or changes in vocalization caused by airway inflammation.

Weakness, collapse, seizures, or bright red mucous membranes can indicate carbon monoxide poisoning, which is a medical emergency that requires immediate treatment.

Triage All Smoke Exposures Immediately

Immediate and aggressive intervention is needed for patients presenting with:

  • Dyspnea
  • Cyanotic mucous membranes
  • Collapse
  • Persistent coughing
  • Loss of consciousness
  • Burns around the face

Early identification of smoke inhalation is key because prompt treatment significantly improves the chances of recovery and helps reduce the risk of permanent lung damage.

Treatment and Monitoring

Focus first on restoring adequate oxygen levels and stabilizing the patient’s airway. Most affected animals benefit from supplemental oxygen. Use masks, nasal cannulas, or oxygen cages depending on the size and temperament of the patient

Depending on the severity of exposure, consider:

  • Thoracic radiographs
  • Blood gas analysis
  • Intravenous fluids
  • Bronchodilators
  • Nebulization
  • Anxiolytics
  • Additional supportive care

More severely affected patients require ongoing hospitalization for continuous monitoring of their respiratory status and ongoing interventions. Extremely severe cases might necessitate intubation and ventilation.

Because lung injury often progresses over several days, even animals with mild to moderate signs of smoke inhalation frequently remain hospitalized for observation despite initially appearing stable.

Protecting Pets During Wildfire Season

Preventing smoke exposure whenever possible is vastly preferable to treating smoke inhalation. Educate pet owners to keep pets indoors with windows and doors closed, limit walks to brief bathroom breaks, and avoid strenuous exercise until air quality improves.

Running a HEPA air purifier can reduce indoor particulate matter, while providing adequate fresh water helps support normal respiratory function. Monitoring your local Air Quality Index (AQI) provides a useful guide for deciding when outdoor activities become unsafe. A good rule of thumb: if conditions are considered unhealthy for people, they are also unhealthy for companion animals.

Staying Prepared Saves Lives

Wildfires often spread with little warning, making preparation just as important as prevention. Advise owners to include their pets in every evacuation plan by keeping carriers, leashes, medications, food, and medical records readily accessible. Discuss monitoring for early warning signs of smoke inhalation with owners of high-risk patients. Encourage them to seek help sooner, reducing the chance of more severe and difficult to treat critical presentations.

Early Intervention Improves Outcomes

Smoke inhalation remains one of the most common medical emergencies associated with wildfires, but early recognition and prompt veterinary care can make a remarkable difference. Intervening quickly when clinical signs appear can reduce morbidity and mortality during wildfire season.

More from Zuku:

Heat Stroke in Dogs: Recognition, Treatment, & Client Education

Heat stroke is one of the most preventable emergencies encountered in small animal practice, yet it continues to carry significant morbidity and mortality. As global temperatures rise and extreme heat events become more frequent, veterinarians and veterinary technicians increasingly encounter patients presenting with life-threatening hyperthermia and multisystem organ dysfunction.

For students preparing for licensure, heat stroke represents a common emergency that integrates physiology, emergency medicine, critical care, and client communication. Successful management depends on rapid recognition, appropriate cooling, intensive supportive care, and effective client education to prevent recurrence.

Understanding Heat Stroke

Heat stroke occurs when thermoregulatory mechanisms become overwhelmed, resulting in an uncontrolled rise in core body temperature. Unlike uncomplicated hyperthermia, heat stroke triggers widespread cellular injury through direct thermal damage, systemic inflammation, endothelial dysfunction, and impaired tissue perfusion. As core temperature rises, protein denaturation, mitochondrial dysfunction, and activation of inflammatory mediators contribute to progressive organ injury. Left untreated, heat stroke can progress rapidly to:

  • Disseminated intravascular coagulation (DIC)
  • Acute kidney injury
  • Hepatic dysfunction
  • Neurologic impairment
  • Cardiovascular collapse.

Although temperatures above 105.8°F (41°C) are commonly associated with heat stroke, clinicians need to remember that the severity of illness depends on both the duration and magnitude of hyperthermia rather than a single temperature threshold.

Which Patients Are at Highest Risk?

Any dog can develop heat stroke under the right conditions, but several patient factors substantially increase the risk.

The dog’s primary method of cooling is evaporative, via panting. This is impaired in brachycephalic breeds, including bulldogs, pugs, and Boston terriers because of congenital airway dysfunction causing chronic upper airway obstruction. Obese patients have reduced heat dissipation because excess adipose tissue provides insulation with reduced functional lung capacity. Geriatric patients, puppies, dogs with cardiovascular or respiratory disease, and animals receiving strenuous exercise during warm weather also demonstrate reduced thermoregulatory reserve.

Environmental conditions often compound these intrinsic risk factors. High humidity significantly limits evaporative cooling. This makes even moderate ambient temperatures dangerous during vigorous activity. Confinement in vehicles where internal temperatures rise rapidly remain one of the most common, devastating, and preventable causes of severe heat stroke.

Clinical Presenation

The earliest clinical signs often reflect compensatory efforts to dissipate heat. Dogs initially present with:

  • Excessive panting
  • Hypersalivation
  • Tachycardia
  • Bright red mucous membranes
  • Restlessness.

As hyperthermia progresses, compensatory mechanisms fail and systemic damage become apparent. Affected patients may develop:

  • Progressive weakness
  • Ataxia
  • Vomiting or diarrhea (often hemorrhagic)
  • Altered mentation
  • Muscle tremors
  • Collapse
  • Seizures
  • Petechiation or spontaneous bleeding secondary to DIC
  • Coma

Hypotension, arrhythmias, respiratory distress, and evidence of multiple organ dysfunction indicate advanced disease and carry a guarded prognosis.

Diagnostic Evaluation

Although treatment must begin immediately, a complete diagnostic workup remains essential for identifying complications and guiding ongoing therapy.

Initial evaluations include a complete blood count, serum biochemistry profile, electrolyte assessment, coagulation testing, blood gas analysis, thoracic radiographs, and urinalysis. Elevated creatine kinase (CK) may indicate concurrent muscle injury, while increased alanine aminotransferase (ALT) reflects hepatocellular injury. Azotemia, electrolyte abnormalities, hypoglycemia, and coagulation abnormalities commonly develop during hospitalization in severe cases.

Continuous monitoring of body temperature, blood pressure, electrocardiography, urine output, neurologic status, plus frequent rechecks of blood glucose, PCV/TS, clotting profiles, and electrolytes, allows early detection of evolving complications.

Treatment Priorities

Management begins with immediate but controlled cooling. Evaporative cooling using cool (not ice-cold) water combined with directed airflow remains the recommended first-line approach. Avoid ice water immersion because peripheral vasoconstriction may impair heat dissipation and complicate patient monitoring. Intravenous fluids also help cool the patient.

Continue cooling until the patient’s core temperature reaches approximately 103°F (39.5°C) to avoid rebound hypothermia. Patients frequently need heat support to maintain a normal temperature after initial cooling and thermoregulatory mechanisms remain disturbed. Simultaneously, clinicians need to initiate aggressive supportive care, including intravenous crystalloid therapy, oxygen supplementation when indicated, correction of electrolyte abnormalities, analgesia, and treatment of complications as they arise.

Frequent reassessment is essential because the systemic effects of heat stroke continue after cooling. Complications such as DIC, acute kidney injury, ARDS, hepatic injury, cardiac arrhythmias, and worsening neurologic dysfunction may develop many hours after the patient’s core temperature has returned to normal. Patients with these conditions require intensive care.

Prognosis

Outcome depends on the duration of hyperthermia, the degree of organ dysfunction, and the speed with which treatment begins. Patients that remain neurologically normal and receive rapid cooling generally have a favorable prognosis. In contrast, delayed presentation, persistent neurologic abnormalities, hypotension, hypoglycemia, DIC, and multiple organ dysfunction syndrome (MODS) significantly worsen survival.

Client Education: Prevention is Best

Heat stroke is a veterinary emergency that educated owners can almost always prevent entirely. Every member of the veterinary team plays an important role in reinforcing heat safety during wellness visits, discharge appointments, and seasonal client communications:

  • Owners need to understand that they must never leave a dog unattended in a parked vehicle, even for a few minutes. Interior vehicle temperatures can rise to life-threatening levels rapidly, even when outdoor temperatures seem mild or windows remain partially open.
  • Exercise recommendations also change during warmer months. Encourage owners to schedule walks during the early morning or late evening, avoid strenuous activity during periods of high heat or humidity, and provide frequent access to shade and fresh water.
  • The following require even greater caution: brachycephalic breeds; obese, geriatric, or very young dogs; and patients with underlying respiratory or cardiovascular disease. Owners should learn to recognize early warning signs, including excessive panting, weakness, and collapse, and seek immediate veterinary care.
  • Spring wellness appointments also provide an ideal opportunity to discuss environmental modifications such as cooling mats, adequate ventilation, and limiting outdoor exposure during heat advisories.

These conversations not only reduce emergency presentations, but also strengthen client trust and reinforce the veterinary team’s role in preventive medicine.

Veterinary Teams Play a Critical Role in Heat Stroke Prevention & Care

As temperatures rise, veterinarians and veterinary technicians have an important opportunity to educate pet owners about preventing heat stroke and recognizing the early clinical signs. Through proactive client education, rapid intervention, and comprehensive supportive care, veterinary teams can help reduce the risk of life-threatening complications and improve outcomes for dogs affected by this preventable emergency.

More from Zuku:

Upper vs. Lower Respiratory Disease: A VTNE® Study Guide

Respiratory disease is a common presentation in small animal practice, and veterinary technicians play an essential role in identifying early clinical signs. One of the most important skills for VTNE® preparation and clinical practice is learning to localize respiratory disease to either the upper or lower respiratory tract using observable clinical signs.

Recognizing upper vs. lower disease allows technicians to assist veterinarians with triage decisions, diagnostic planning, and patient stabilization. Respiratory distress can rapidly become life-threatening, so quick recognition and action is critical.

Understanding the Anatomy of the Respiratory Tract

Think of the respiratory system as comprised of two major sections.

The upper respiratory tract (URT) includes the nose, nasal passages, sinuses, pharynx, and larynx. These structures primarily function to filter, warm, and humidify inhaled air.

The lower respiratory tract (LRT) includes the trachea, bronchi, bronchioles, and alveoli. These structures both facilitate airflow into the lungs and allow gas exchange.

Clinical signs help determine which region of the respiratory tract is affected, allowing the veterinary team to narrow the differential diagnoses early in the evaluation process.

Clinical Signs of Upper Respiratory Disease

Disease of the URT commonly produces nasal discharge, sneezing, increased inspiratory effort/time, and/or respiratory noise (stridor/high-pitched or stertor/low-pitched).

Technicians should assess several characteristics of nasal discharge:

  • Color: serous (clear/watery), mucoid (cloudy/white), purulent (thick and yellow/green), or hemorrhagic (red/bloody – called “epistaxis”)
  • Odor
  • Unilateral vs. bilateral

For example, unilateral purulent discharge may suggest a nasal foreign body or tumor and is more likely to have a foul odor. Bilateral mucoid discharge may indicate infectious or inflammatory disease. Epistaxis can occur with nasal tumors, fungal infections such as aspergillosis, or systemic diseases affecting platelet function.

Clinical Signs of Lower Respiratory Disease

Disease of the LRT typically causes dyspnea (difficulty breathing), tachypnea (rapid breathing), and pale or cyanotic gums if severe.

Dyspneic patients may appear anxious or reluctant to move and exhibit:

  • Increased respiratory effort (dyspnea)
  • Rapid breathing (tachypnea)
  • Abdominal involvement during respiration
  • Nasal flaring and/or neck stretching

Common causes of dyspnea include:

  • Tracheal collapse/narrowing
  • Congestive heart failure
  • Feline asthma
  • Pneumonia
  • Pleural effusion

Because dyspnea can quickly become life-threatening, veterinary teams must stabilize these patients with oxygen therapy and anxiolytics (to help calm them) before diagnostic imaging or other procedures. The stress of restraint for diagnostics in a dyspneic patient can be enough to cause respiratory failure and death.

Remember, tachypnea may occur independently of respiratory disease, occurring secondary to pain, stress, or metabolic disorders. Rule out primary respiratory distress prior to looking for other causes.

Overlapping Clinical Presentations

Some clinical signs do not localize easily to one portion of the respiratory tract.

Coughing is a classic example. It can occur with upper respiratory diseases such as infectious tracheobronchitis (kennel cough) or with lower airway conditions such as feline asthma.

Veterinary technicians must also recognize that pet owners frequently misinterpret coughing episodes in cats as hairball vomiting. A coughing cat typically crouches with its neck extended and produces repeated cough sounds, rather than the abdominal contractions seen with vomiting. Similarly, dogs with tracheobronchitis often bring up mucous at the end of their cough, which owners may erroneously describe as vomiting.

Another consideration is patients with concurrent upper and lower respiratory disease. An example could be a patient with an upper respiratory viral infection that compromised the respiratory defenses and lead to bacterial pneumonia.

Diagnostic Testing for Respiratory Disease

After initial stabilization, several diagnostic tests can help identify the underlying cause of respiratory disease.

Common diagnostic tools include:

  • Thoracic-focused assessment with sonography (TFAST) to detect pleural/pericardial effusions and some parenchymal diseases
  • Thoracic radiographs to evaluate lung patterns, heart, trachea, mediastinum, and other intrathoracic structures
  • Pulse oximetry to measure oxygen saturation levels
  • Infectious disease testing, including heartworm testing and PCR for respiratory pathogens
  • Arterial blood gas to determine blood oxygenation

Advanced diagnostics may include thoracocentesis, CT imaging, rhinoscopy, or bronchoscopy, depending on the Ddx list.

From Clinical Signs to Diagnosis: The Technician’s Role

By carefully evaluating airway signs, technicians can help localize disease within the respiratory tract and assist the veterinary team in making timely diagnostic and treatment decisions.

Mastering respiratory clinical sign recognition improves VTNE® readiness and allows veterinary technicians to contribute more effectively to patient assessment and care.

More from Zuku Review:

Polyuria, Polydipsia, Dysuria, and Pollakiuria: Essential Urinary Terms for the VTNE®

Changes in urination are a common reason pet owners bring their animals to a veterinary clinic. For veterinary technicians preparing for the VTNE®, understanding the terminology used to describe urinary abnormalities is essential for success.

Four key terms frequently appear in clinical records and exam questions: polyuria, polydipsia, dysuria, and pollakiuria.

Each term describes a specific type of urinary abnormality and helps veterinary teams determine whether the kidneys, urinary bladder, or another body system is the cause of the urinary signs.

Understanding Urinary Terms for VTNE® Success

Accurate terminology allows veterinary professionals to communicate clinical findings clearly and efficiently. A technician needs to use the correct medical term when recording patient history or observations in order to help the veterinary team quickly understand the nature of the problem.

Many urinary conditions share similar presenting complaints, so precise descriptions of urination patterns are essential for narrowing the list of possible diagnoses.

Polyuria and Polydipsia (PU/PD)

Polyuria refers to the production of abnormally large volumes of urine. Animals with polyuria often urinate more frequently simply because their bladder fills more rapidly.

Polyuria commonly occurs alongside polydipsia, which means excessive thirst and water consumption.

Together, these two findings are commonly abbreviated as PU/PD. Many systemic diseases can interfere with the kidneys’ ability to properly regulate water balance in the body and result in PU/PD, including:

  • Kidney disease
  • Diabetes mellitus
  • Cushing syndrome (hyperadrenocorticism)
  • Hyperthyroidism
  • Certain medications (e.g., glucocorticoids and diuretics)

Owners may notice signs such as increased water consumption, more frequent trips outside, having to clean the litter box more often, or inappropriate urination inside the home.

While PU/PD involves excessive urine volume, dysuria and pollakiuria describe problems associated with voiding urine.

Dysuria refers to painful or difficult urination. Animals with dysuria may strain to urinate (stranguria), vocalize, or produce only small amounts of urine.

Pollakiuria refers to frequent attempts to urinate, typically producing very small volumes each time.

These signs often occur together and may indicate irritation or inflammation of the bladder or urethra.

Common Diseases Associated with Urinary Clinical Signs

Many diseases can produce dysuria and pollakiuria in dogs and cats.

A condition we frequently see in cats is feline lower urinary tract disease (FLUTD). This syndrome includes several disorders affecting the bladder and urethra. FLUTD can cause:

  • Dysuria
  • Pollakiuria
  • Hematuria
  • Urinary obstruction (almost exclusively a male cat issue where a plug of debris secondary to the inflammation obstructs the urethra)

Urolithiasis, or the formation of urinary stones, is another important cause of urinary tract disease. Stones may develop within the urinary bladder (cystic calculi) or kidneys (nephroliths). The most common stone types in dogs and cats are magnesium ammonium phosphate (struvite) and calcium oxalate.

An additional cause is bacterial cystitis, which is inflammation of the urinary bladder due to infection.

Diagnostic Tests for Urinary Disease

Veterinary teams use several diagnostic tools to evaluate urinary disease.

Urinalysis is one of the most important tests. It evaluates urine concentration (urine specific gravity or USG), chemical composition (via dipstick), and sediment (microscopy).

The USG is critical to assess kidney function. If the USG falls between 1.008 and 1.012, the urine is considered isosthenuric, meaning the kidneys are not concentrating the urine effectively.

The dipstick quickly assesses for the presence of protein, red and white blood cells, ketones, glucose, etc. in the urine plus estimates pH. Sediment evaluation identifies crystals, casts, bacteria, and types of cells present in the urine.

Veterinarians often interpret urinalysis results alongside serum chemistry panels, which measure markers of kidney function such as blood urea nitrogen (BUN), creatinine, and symmetric dimethylarginine (SDMA). Electrolytes, such as potassium, calcium, phosphorus, and sodium, are also important when evaluating diseases of the urinary tract.

Additional diagnostics may include:

  • Urine culture and sensitivity testing to identify bacterial infections and appropriate antibiotics
  • Abdominal radiographs to detect radiopaque urinary stones
  • Abdominal ultrasound to evaluate the kidneys and urinary bladder

Together, these tests help determine the underlying cause of urinary abnormalities and guide treatment decisions. Advanced testing might include contrast cystogram, excretory urogram, uroscopy, or CT.

The Veterinary Technician’s Role in Identifying Urinary Disease

Understanding urinary clinical terminology is essential for veterinary technicians and VTNE® candidates.

By recognizing the differences between polyuria, polydipsia, dysuria, and pollakiuria, technicians can accurately document patient findings and assist veterinarians in identifying urinary tract disease.

Mastering these terms not only supports exam preparation but also improves communication and patient care in everyday veterinary practice.

More from Zuku Review:

Stertor vs. Stridor in Dogs and Cats: A Clinical Guide for Vet Techs

Abnormal respiratory sounds often provide valuable diagnostic clues in veterinary practice. For veterinary technicians preparing for the VTNE®, it is very important to be able to distinguish between stertor and stridor.

Both sounds indicate upper airway compromise but they originate from different parts of the upper respiratory tract and suggest different underlying causes. Learning to distinguish these sounds helps technicians assist veterinarians with clinical localization and rapid patient assessment for best treatment outcomes.

What Is Stertor?

Stertor is a low-pitched respiratory noise often described as snoring, often audible during both inspiration and expiration.

This occurs when airflow passes by abnormal/narrowed soft tissues in the upper airway (particularly obstruction of the nasal passages, soft palate, or pharynx) causing vibration of the tissues.

Common Causes of Stertor

Several conditions can produce stertor in veterinary patients.

One common cause is nasopharyngeal polyps in cats. These inflammatory growths develop from the mucosal lining of the tympanum, pharynx, or auditory tube and partially obstruct airflow if they extend into the nasopharynx.

Stertor also occurs frequently in brachycephalic dog breeds, such as bulldogs (American or French) and pugs. These breeds classically have anatomical abnormalities collectively known as “brachycephalic airway syndrome.”

Common features of brachycephalic airway syndrome include:

  • Elongated soft palate
  • Narrow nostrils (stenotic nares)
  • Everted laryngeal saccules
  • Hypoplastic trachea

What is Stridor?

Stridor is a high-pitched, harsh respiratory sound caused by a narrowing of a large, rigid airway structure such as the larynx or trachea.

The sound often resembles a whistle or squeal and often is louder during inspiration when airflow increases.

Common Causes of Stridor

Several diseases can produce stridor in dogs and cats.

One of the most recognized causes is laryngeal paralysis, a condition in which the nerves responsible for opening the larynx during inspiration fail. Instead of actively retracting during inspiration, the arytenoid cartilages remain flaccid and the negative pressure of inspiration further pulls the tissues inward. This causes airflow restriction and a characteristic high-pitched sound.

Another important cause is tracheal collapse, which commonly affects small breed dogs such as Yorkshire terriers and Pomeranians. The cartilage rings that normally support the trachea weaken and flatten, narrowing the airway during inspiration and producing a distinctive wheezing or honking sound.

Other potential causes of stridor include airway tumors, foreign bodies, or severe inflammation.

A Core Triage Skill for Veterinary Technicians

Veterinary technicians are often the first members of the veterinary team to observe abnormal respiratory sounds during their initial patient assessment.

Recognizing the difference between stertor and stridor can help technicians:

  • Localize respiratory disease within the airway
  • Identify potentially life-threatening obstructions
  • Communicate critical findings to the veterinarian
  • Prioritize triage and stabilization

In patients with severe respiratory distress, rapid recognition of airway obstruction can be essential in initiating appropriate therapy.

The Veterinary Technician’s Role in Identifying Airway Obstruction

Stertor and stridor both indicate airway obstruction, but they arise from different regions of the respiratory tract and suggest different underlying diseases.

By learning to recognize these sounds and understanding their clinical significance, veterinary technicians improve diagnostic accuracy, better assist with emergency triage, and strengthen their VTNE® exam preparation.

More from Zuku Review:

Mastering Cardiac Disease for the VTNE®: What Every Vet Tech Needs to Know

Cardiac disease is a common condition in veterinary medicine and an important topic on the VTNE®. Veterinary technicians must recognize early indicators of heart disease and understand how common cardiac conditions present in dogs and cats.

The three most common diseases in both clinical practice and exam questions are myxomatous mitral valve degeneration (MMVD), dilated cardiomyopathy (DCM), and hypertrophic cardiomyopathy (HCM). Understanding these conditions helps technicians identify abnormal findings during physical examinations and assist with diagnostic testing and patient monitoring.

The Veterinary Technician’s Role in Identifying Cardiac Disease  

Many patients with early heart disease initially appear healthy. Veterinary teams often detect abnormalities only during a physical examination or with a detailed history.

Veterinary technicians play a key role in identifying these subtle findings. Detecting abnormalities such as heart murmurs, abnormal pulse quality, or arrhythmias can prompt further diagnostic evaluation.

Recognizing subclinical cardiac disease allows the veterinary team to begin monitoring or treatment before patients progress to congestive heart failure (CHF).

Once CHF develops, animals commonly present with clinical signs such as coughing, exercise intolerance, lethargy, collapse, or respiratory distress.

Myxomatous Mitral Valve Degeneration (MMVD) 

Myxomatous mitral valve degeneration is the most common cardiac disease in dogs, particularly in older small and medium-sized breeds.

This condition occurs when the mitral valve leaflets become thickened and distorted. As the valve degenerates, it fails to close properly during systole. This means blood leaks backward from the left ventricle into the left atrium, creating turbulent blood flow. This turbulence produces the characteristic heart murmur often detected during physical examination.

Over time, the condition can progress to left-sided congestive heart failure, resulting in pulmonary edema and respiratory distress.

Dilated Cardiomyopathy (DCM)

Dilated cardiomyopathy most commonly affects large and giant breed dogs, including Doberman pinschers, Great Danes, and Irish wolfhounds.

In DCM, the heart muscle becomes weakened and stretched, decreasing contractility. The ventricular chambers enlarge in an attempt to compensate for the decreased cardiac output. Because the dilated heart cannot effectively pump blood forward, fluid may accumulate within the lungs or body cavities. Arrhythmias are also common.

Some dogs with DCM may not have a heart murmur, which can make early detection challenging. Owners might report exercise intolerance, episodes of collapse, or weakness. Patients are sometimes first diagnosed only when they develop congestive heart failure with pulmonary edema, pleural effusion, or abdominal fluid accumulation.

Hypertrophic Cardiomyopathy (HCM)

Hypertrophic cardiomyopathy is the most common heart disease in cats.

In HCM, the walls of the left ventricle become abnormally thickened, reducing the chamber size and limiting proper filling during diastole. As a result, the heart pumps less blood to the body, which eventually backs up and dilates the left atrium. Cats with HCM may or may not have obvious abnormalities during auscultation. Some develop heart murmurs or gallop rhythms, while others show no detectable abnormalities on physical exams. Additionally, about 50% of murmurs noted in cats are non-pathologic (innocent murmurs), making their detection fairly non-specific for disease.

Cats with HCM can develop CHF (pulmonary edema and/or pleural effusion), fatal arrhythmias, or formation of blood clots within the left atrium.

One serious complication of feline HCM is arterial thromboembolism (ATE). In this condition, a blood clot forms within the dilated left atrium, travels through the bloodstream, and obstructs a major artery. The most common site of obstruction is the aortic trifurcation, producing an extremely painful condition commonly called a “saddle thrombus.”

Diagnostic Tests for Cardiac Disease

Several diagnostic tests help veterinarians evaluate cardiac disease in dogs and cats.

Thoracic radiographs provide information about heart size and shape. They can also reveal evidence of pulmonary edema or pleural effusion. The vertebral heart score, calculated on radiographs, objectively assesses heart enlargement.

Electrocardiography (ECG) evaluates the heart rhythm and identifies arrhythmias and abnormalities in the complex appearance.

Blood tests are available to screen for myocardial damage and identify patients in need of further workup.

Echocardiogram, an ultrasound of the heart done by a cardiologist, is considered the gold standard diagnostic test for cardiac disease. The veterinarian can visualize and measure heart chambers, valves, and blood flow in real time.

Elevating Patient Care through Cardiac Knowledge

Cardiac disease is a common and clinically important topic for veterinary technicians and VTNE® candidates.

Understanding the key features of myxomatous mitral valve degeneration, dilated cardiomyopathy, and hypertrophic cardiomyopathy allows technicians to recognize concerns in both the history and examinations and best assist with appropriate diagnostic testing.

These skills improve both VTNE® performance and patient care in everyday veterinary practice.

More from Zuku Review:

Chocolate Toxicosis in Dogs: A Common Valentine’s Day Emergency

Valentine’s Day brings an increased risk of chocolate exposure for dogs. Boxes of truffles, candy bars, and baked goods often sit within reach, and even well-meaning owners underestimate the danger. Chocolate toxicosis remains one of the most common food-related toxicoses in small animal practice, and dogs represent the vast majority of cases.

Understanding how chocolate causes toxicosis and the need for quick intervention can minimize the risk of life-threatening complications.

The Dangers of Chocolate

Chocolate contains methylxanthines, primarily theobromine and (usually smaller amounts of) caffeine, which dogs metabolize slowly. These compounds stimulate the central nervous system, increase myocardial contractions and gastric secretions, and cause diuresis. As toxin concentrations increase, clinical severity escalates.

Not all chocolates pose equal risk. Darker chocolate contains significantly higher concentrations of methylxanthines, making baking chocolate and dark chocolate far more dangerous than milk chocolate. Since severity depends on the percentage of cacao and the dog’s weight, even relatively small amounts can cause toxicosis in small-breed dogs.

Dose-Dependent Clinical Signs

Chocolate toxicosis follows a predictable, dose-dependent pattern:

  • Low doses cause vomiting, diarrhea, restlessness, and polydipsia
  • Moderate doses lead to agitation, tremors, tachycardia, and ventricular premature contractions (VPCs)
  • High doses can result in seizures, secondary hyperthermia, hypertension, severe arrhythmias, respiratory failure, coma, and death

Cardiac abnormalities, particularly VPCs, represent a hallmark of more severe toxicosis and require close ECG monitoring.

Timeline of Intoxication

Most dogs develop clinical signs within 6-12 hours of ingestion. If a patient remains asymptomatic beyond that window, the likelihood of severe toxicosis decreases. However, once clinical signs appear, they can persist for up to 72 hours, particularly in higher-dose exposures. Thus, it is critical to treat exposure as a time-sensitive emergency.

Diagnostic Approach: Exposure Tells the Story

Diagnosis relies heavily on known or suspected exposure. Physical evidence often supports exposure, as vomitus may carry a characteristic chocolate odor and contain visible chocolate fragments or wrappers.

In moderate to severe cases, clinicians should prioritize:

  • Continuous ECG monitoring to detect arrhythmias or persistent tachycardia
  • Blood pressure assessment for hypertension
  • Evaluation of acid–base status and electrolytes

Laboratory testing aids ongoing patient management, but exposure history remains the cornerstone of diagnosis.

Treatment Priorities for Chocolate Toxicosis

Chocolate toxicosis has no antidote, so treatment focuses on decontamination and supportive care:

  • Induce emesis when ingestion is recent and the patient remains asymptomatic
  • Consider activated charcoal in select cases to limit ongoing absorption
  • Initiate IV fluids to support cardiovascular stability and promote elimination
  • Use methocarbamol to control tremors and benzodiazepines for seizures
  • Treat ventricular arrhythmias promptly with appropriate anti-arrhythmics

Severely affected patients may require intensive monitoring, supportive care, and on-going treatment for several days. Early recognition of complications improves outcomes.

Complications to Monitor For

Chocolate products often also contain high levels of fat and sugar. As a result, affected patients may develop pancreatitis days after ingestion, even when neurologic and cardiac signs resolve/don’t occur. Inform owners of the clinical signs that warrant a recheck and consider proactively beginning GI supportive medications and low-fat bland diets.

Valentine’s Day: A Day for Love & Prevention Education

The prognosis for chocolate toxicosis remains good in the vast majority of cases, including many that require hospitalization. Severity depends on the type and amount of chocolate, patient size, and speed of intervention.

Valentine’s Day offers an ideal opportunity for client education. Clear guidance on keeping chocolate out of reach can prevent emergencies before they happen—and spare both patients and owners unnecessary distress. Help your pet parents show their love on Valentine’s Day AND ace your toxicology questions by knowing these chocolate toxicosis facts.

More from Zuku:

Feline Urethral Obstruction: A Succinct Guide for Quick & Confident NAVLE® Decisions

Feline urethral obstruction (UO) is one of the most common and urgent conditions you will encounter in clinical practice, and it is a NAVLE® classic. Most often seen in young adult male cats, it is a blockage of the urethra that prevents normal urine flow and can rapidly lead to life-threatening hyperkalemia and acute kidney injury. Caused primarily by urethral plugs associated with feline lower urinary tract disease (FLUTD)/feline interstitial cystitis (FIC), though uroliths and other less common disorders are possible. Fast recognition and intervention directly determine morbidity and mortality by preventing severe metabolic and cardiovascular complications. A structured approach helps treat with confidence, as over 90% of cats survive to discharge. In this article, you’ll get an overview of how to recognize a pattern on the NAVLE® for diagnosis, stabilization, treatment, and long-term prevention.

Why Rapid Recognition is Necessary

Blocked cats often present with nonspecific clinical signs such as anorexia, vomiting, and depression. Sometimes owners report more specific urinary signs such as stranguria, dysuria, and hematuria. Hallmark physical exam findings include palpating a firm, painful, and distended urinary bladder, often along with dehydration +/- bradycardia.

UO causes rapid over-distension of the bladder, leading to bladder damage and even risk of rupture. This increased pressure is transmitted to the kidneys causing reduced blood flow and filtration, leading to rapidly rising potassium, metabolic acidosis, and azotemia. Without aggressive treatment, obstructed cats can develop fatal bradyarrhythmias within 24+ hours. While female cats can exhibit signs of FIC (e.g., dysuria), the long urethras of male cats that narrow sharply near the penile tip means that urethral plugs formed secondary to lower urinary track edema +/- crystalluria cause UO.

Focus on the Big Three Diagnostic Priorities 

The NAVLE® asks about blocked cats, focusing on your ability to identify the most urgent diagnostics. Prioritize:

  1. Potassium: Hyperkalemia is the most immediate threat given the risk of cardiac arrest as arrhythmias worsen. IV calcium gluconate is temporarily cardioprotective. Used by itself, or in conjunction with short-acting insulin and dextrose CRI, terbutaline, or bicarbonate, all of which transiently reduce circulating potassium. 
  2. Renal Values: Post-renal azotemia, acute kidney injury (AKI), dehydration, and shock all contribute to azotemia and hyperphosphatemia. Relieving the obstruction and using IV crystalloids to rehydrate and promote filtration resolves azotemia in most cases.
  3. ECG: As potassium rises to dangerous levels, ECG changes include tall, tented T waves, blunted or absent P waves (i.e., atrial standstill), and subsequent bradycardia. Occasionally cats present with normal heart rates due to sympathetic activation, but ECG changes persist.

Supplemental diagnostics, such as a CBC, full biochemistry, blood gas, focused ultrasound evaluation, and blood pressure are also important components of the initial evaluation.

Effectively Triage and Stabilize

Immediate Analgesia

Blocked cats are in severe pain. Use full µ-agonist opioids (e.g., methadone, hydromorphone), or buprenorphine if a pure µ-agonist is not available. Avoid NSAIDs since these patients already risk renal compromise.

Stabilization Prior to Unblocking

Place an IV catheter and begin fluids. Review initial diagnostics and treat hyperkalemia if present. Address indicators of shock, including low blood pressure or hypothermia. Always consider decompressive cystocentesis once sedated (or at presentation if moribund – the key is the cat must be still) to both provide rapid relief of bladder distension and reduce urethral pressure, thus facilitating catheter passage.

Sedation and Catheterization

Use anesthesia for catheterization, with drug choice dependent on patient severity. Benzodiazepines help reduce spasm. A coccygeal epidural can lower anesthetic requirements and improve catheterization success. Use soft, well-lubricated catheters and very gentle manipulation. Suture short-term indwelling catheters in place with closed urinary collection systems to continue drainage. Use physiologic saline to gently lavage the bladder after de-obstruction.

Next Diagnostic Steps

After stabilization and de-obstruction, undertake further diagnostics to complete the workup. Abdominal radiographs confirm proper catheter placement and check for radiopaque uroliths. Full urinalysis +/- culture (sample taken from the catheter prior to flushing) evaluates for infection and crystals.

Importance of Post-Obstruction Management

Continue IV crystalloids, analgesia (buprenorphine +/- gabapentin), and recheck blood work until normalized. Monitor electrolytes frequently (every two to four hours until normalized, then every eight to twelve). Repeat blood gas to monitor for resolution of acidemia if initially concerning. Check renal values every 24 hours.

Post-obstructive diuresis can be dramatic. Monitor urine output every one to two hours, and match losses with IV fluid administration to prevent dehydration and keep up with diuresis. Adjust rates as the cat stabilizes. Reduce in-hospital stressors as much as possible, with medications, environment, and handling considerations.

Four Signs It’s Time to Remove the Urinary Catheter

After at least 24 hours of catheterization, there are four important factors that help determine when to attempt urinary catheter removal:

  1. The urine must be clear (no longer bloody or cloudy)
  2. Urine output normalized
  3. IV fluid rate weaned
  4. Azotemia resolved

Ensure the patient can fully and comfortably void his bladder after urinary catheter removal. Consider urine culture post-catheter removal in case of iatrogenic infection. Discharge on short-term oral analgesics +/- antibiotics as indicated.

Preventing Reoccurrence is Multifactorial 

Blocked cats have a 50% lifetime recurrence risk. Warn owners of the risks/signs of re-obstruction and discuss ways to increase the chances of prevention. Prevention strategies include increasing water intake (wet food, fountains, multiple bowls), reducing stress (especially environmental changes, such as number and cleanliness of litterboxes), and using prescription urinary diets when crystals are present.

Cats who experience repeated episodes of obstruction are candidates for perineal urethrostomy (PU), but due to the invasive nature and possible complications, this surgery is not a first-line treatment option. Cats with uroliths need a cystotomy for stone removal AFTER full stabilization and resolution of bloodwork abnormalities. Perform cystotomy prior to urinary catheter removal, given the immediate risk of re-obstruction. Stone analysis after removal dictates the type of life-long prescription diet necessary for these cats.

Instruct owners that stress is the primary driver of FIC and provide them many environmental, dietary, and pharmacological options to aid in prevention.

More on Feline Urethral Obstruction for Subscribers:

More from Zuku: